

Medicaid Pennsylvania Timely Filing Limit: 180 Days, 365 Days and the Exceptions
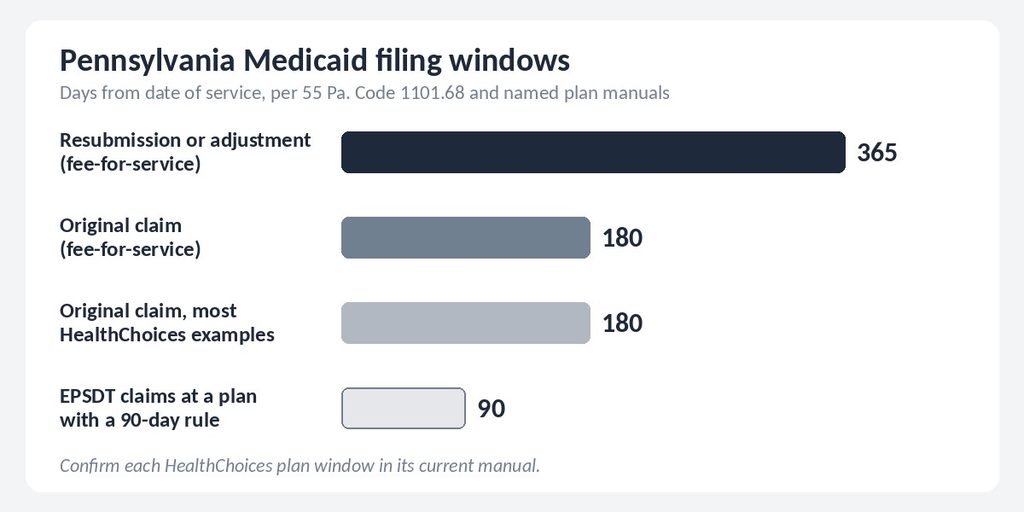
The Medicaid Pennsylvania timely filing limit is 180 days from the date of service for original fee-for-service claims, under 55 Pa. Code Section 1101.68. Rejected claims and adjustments must be received within 365 days of service. HealthChoices managed care plans set windows by contract, and some apply shorter periods to specific services.
Practices that bill Pennsylvania Medicaid often meet three numbers in one week: 180 days, 365 days and sometimes 90 days. Each number is correct for a different claim type or payer. This guide explains which clock governs fee-for-service and HealthChoices claims, how to request an exception, and how to calculate a deadline for a specific claim. A self-check near the end shows where a billing process may be exposed.
Key Numbers: Pennsylvania Medicaid Filing Windows
| Metric | Practical target/range | Review frequency | Source type |
| Original claim, fee-for-service | 180 calendar days from date of service | At each regulation or handbook update | Regulation (R) |
| Original claim, nursing facility or ICF | 180 days from the last day of the billing period | At each regulation or handbook update | Regulation (R) |
| Resubmission of a rejected original claim, or a claim adjustment | 365 days from date of service | Weekly rejection queue | Regulation (R) |
| 180-day exception request | Within 60 days of the eligibility determination or third-party response date | When either notice arrives | DHS guidance (A) |
| Claim missing from remittance advice | Resubmit if absent after 45 days | Weekly | DHS guidance (A) |
| HealthChoices plan examples | 180 days initial; 365 days corrections; 90 days for some EPSDT claims | At each plan manual update | Plan manual (M) |
| Internal submission target | Most claims filed within about 10 days of service | Weekly | Practical target (P) |
| Internal alert point | Flag unbilled claims at 50% of the window, about day 90 (day 45 for a 90-day rule) | Weekly | Practical target (P) |
Source labels: R = Pennsylvania regulation, 55 Pa. Code Section 1101.68, as restated by the Department of Human Services (DHS). A = DHS guidance. M = managed care plan manual or provider page. P = practical target commonly used in billing operations; Pennsylvania Medicaid does not require it. EPSDT = Early and Periodic Screening, Diagnosis and Treatment.
How Many Days Does Pennsylvania Medicaid Allow for an Original Claim?
Pennsylvania Medicaid fee-for-service providers must submit original invoices so that the Department receives them within 180 days after the date of service, according to 55 Pa. Code Section 1101.68. The rule counts calendar days. The DHS billing and claims FAQ repeats the same limit for claims processed through the PROMISe system.
Fee-for-service claims: 180 calendar days
The key word in the regulation is “received.” A claim counts only when the Department has received it, and a claim that never reaches a remittance advice can still be late. The federal ceiling under 42 CFR 447.45 is 12 months, and Pennsylvania set a shorter period. Count from the date of service, and file well before day 180 when paper mailing or a clearinghouse adds time.
Nursing facilities and ICFs: the billing period rule
Nursing facility and ICF/MR providers count differently. They must submit original claims within 180 days of the last day of a billing period, which covers services provided to a recipient during one calendar month. A facility that anchors its tracking to individual service dates may misread both the original deadline and the resubmission deadline, because both use the billing period as the starting point.
Resubmissions and adjustments: 365 days
A rejected original claim, or a claim adjustment, must be received within 365 days of the date of service. Nursing facilities and ICF/MR providers use 365 days from the last day of each billing period. This longer window is easy to misread. It does not extend the deadline for a first submission, and a claim that was never submitted within 180 days is not rescued by it.
Does the Medicaid Pennsylvania Timely Filing Limit Change Under HealthChoices?
Often it does not change the headline number, but it does change the details. HealthChoices managed care organizations (MCOs) set filing rules in provider contracts and manuals. A DHS-hosted April 2024 presentation on MCO billing for pharmacists, using Keystone First as its example, says claims must be received by the MCO within a maximum of 180 days, though plan manuals add their own rules for corrections, secondary claims and special services.
The AmeriHealth Caritas Pennsylvania Community HealthChoices billing page lists 180 days for initial claims and 365 days for resubmissions and corrections. It also sets a 60-day window for coordination of benefits submissions after primary payment, and requires the dates and dollar amounts on the explanation of benefits to match the claim. That 60-day figure is far shorter than a fee-for-service habit would suggest.
The UPMC Health Plan manual, Chapter H on claims procedures (updated October 2024), shows how much one plan can vary by claim type. UPMC for You accepts new Medical Assistance claims within 180 days, but EPSDT claims within 90 days. Corrected claims are accepted within 90 days of the remittance date or 365 days of service, whichever is greater, and EPSDT corrections stay at 90 days.
In billing audits, a common pattern is an EPSDT or well-child claim that sits in the general 180-day queue and quietly passes a plan’s 90-day limit. Tag EPSDT claims for a separate deadline when any plan in your contracts applies a shorter window to those services. Pull each plan’s current manual at contract renewal, and record every window in the billing system.
When Can Pennsylvania Waive the 180-Day Limit?
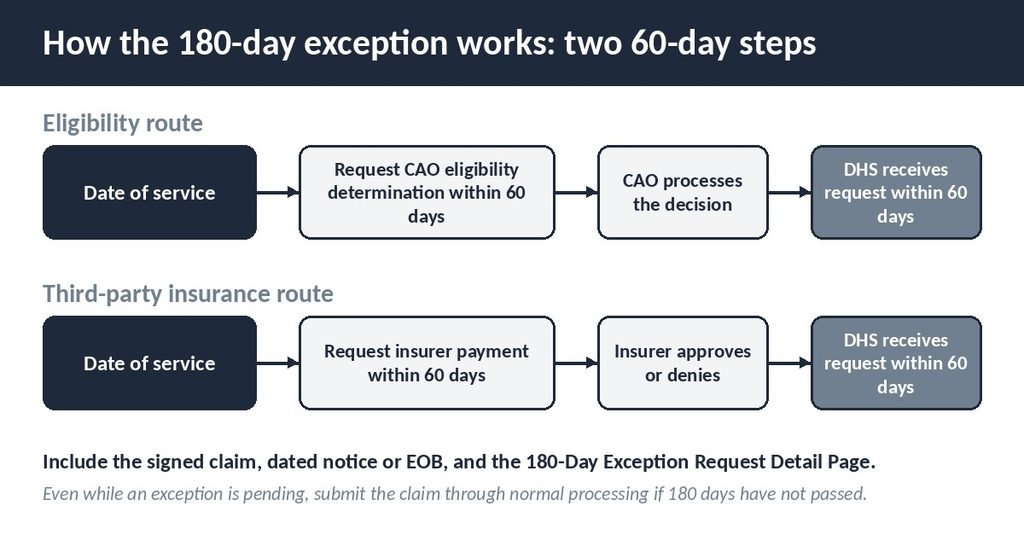
DHS considers a 180-day exception only in two situations: the provider requested an eligibility determination from the County Assistance Office (CAO) within 60 days of the date of service, or the provider requested payment from a third-party insurer within 60 days of the date of service. Each situation has a second 60-day clock for the request itself.
For an eligibility exception, the Department must receive the request within 60 days of the CAO’s eligibility determination processing date. For a third-party exception, the request must arrive within 60 days of the date on the third-party denial or approval. The regulation also states that when a delay stems from a third party or an eligibility determination and 180 days have not passed, the provider should still submit the claim through normal processing.
A complete request includes the claim form with an original signature, supporting documents such as the dated CAO notice or the insurer’s explanation of benefits, and a 180-Day Exception Request Detail Page. DHS describes the steps in the FAQ and in Medical Assistance Bulletin 99-18-08. Mail inpatient and outpatient requests to the Bureau of Fee-for-Service Programs, and send long term care requests to the Office of Long-Term Living.
In billing audits, another common pattern is an eligibility problem discovered at month four. The practice then learns that the first 60-day step, requesting the determination within 60 days of service, was already missed. Ask every self-pay or “pending coverage” patient for Medicaid status when the visit occurs, and start the CAO request within 60 days if coverage is possible. A provider credentialing and enrollment process that keeps PROMISe service locations current also removes one common cause of delays.
How Do You Calculate a Pennsylvania Medicaid Deadline?
The deadline equals the date of service plus the applicable window in calendar days, so a fee-for-service visit on August 12, 2026 must be received by February 8, 2027. The arithmetic is simple. The harder step is choosing the correct window and the correct start date for each claim type.
Formula: Last filing date = clock start date + window in calendar days. The clock starts on the date of service for original claims, on the last day of the billing period for nursing facility claims, and on the remittance, determination or third-party date for exceptions and plan-specific correction rules.
Step-by-step: set the deadline before billing
- Verify eligibility and the plan assignment for the exact date of service, because fee-for-service and each HealthChoices plan differ.
- Identify the claim type, since EPSDT, nursing facility and corrected claims may use different windows.
- Pull the window from the DHS handbook for fee-for-service, or from the current plan manual for managed care.
- Add the window to the clock start date and store the result in the claim record.
- Set an internal alert at half the window, and use a timely filing tracking routine when volume is high.
- File electronically, then confirm the claim appears on a remittance advice.
Worked examples: four clocks from one visit
Illustrative scenario (not an actual client record): a patient is seen on August 12, 2026. The table shows four clocks as of October 3, 2026. Actual dates depend on the claim type, the plan and the notice dates.
| Clock | Formula | Last date | Days left on Oct. 3, 2026 |
| Original fee-for-service claim | Date of service + 180 days | February 8, 2027 | 128 |
| Resubmission of a rejected original claim | Date of service + 365 days | August 12, 2027 | 313 |
| Same visit billed to an EPSDT plan with a 90-day rule | Date of service + 90 days | November 10, 2026 | 38 |
| Exception request after a CAO determination processed September 8, 2026 | Processing date + 60 days | November 7, 2026 | 35 |
Illustrative scenario (not an actual client record): a corrected claim for a March 10, 2026 service receives a plan remittance on August 20, 2026. Under a rule of 90 days from the remittance or 365 days from service, whichever is greater, the corrected claim is due by March 10, 2027, because the service-date window ends later than November 18, 2026.

How Do Medicare, Other Insurance and Secondary Billing Affect the Clock?
Other insurance does not pause the 180-day clock by itself. DHS requires billing Medicare or another third party first, and the exception rule protects a claim only when the provider asked the insurer for payment within 60 days of service and then asked DHS for the exception on time. Keep the explanation of benefits, because DHS rules call for retaining those records for at least four years.
Payer differences matter on mixed panels, because a Pennsylvania practice may bill fee-for-service Medicaid, several HealthChoices plans, Medicare and commercial carriers in the same week. The table compares the main clocks a practice meets, and each one needs its own calendar entry in the billing system.
| Payer or product | Filing window | Source type |
| Pennsylvania Medicaid fee-for-service | 180 days from date of service; 365 days for resubmission | 55 Pa. Code 1101.68 (R) |
| HealthChoices managed care | Plan contract; examples of 180 days initial, 365 days corrections, 60 days COB after primary payment | Plan manuals (M) |
| Original Medicare | 12 months from date of service | Federal rule, 42 CFR 424.44 |
| Medicare Advantage | Plan-specific; confirm in the contract | Plan contract |
| UPMC Health Plan commercial | 365 days from date of service | UPMC manual, Chapter H (M) |
A DHS Benefit Recovery notice states that Medicare Part A and Part B filing limits typically expire one year from the date of service, and it describes recovery of Medical Assistance payments made when Medicare should have been billed first. Our 12-month Medicare filing rule guide covers that limit, and the secondary claim filing deadline guide explains the sequencing.
Other states
Other states use different numbers, and a practice that bills across state lines needs separate calendars. Compare the Texas Medicaid 95-day rule, the Florida Medicaid filing limits and the Medi-Cal filing rules. Many multi-state practices use a medical billing partner to keep those windows separate.
What Happens When a Claim Misses the Window or Never Posts?
A claim past the filing limit denies, and a claim that never appears on a remittance advice may be treated as not received. DHS advises resubmitting any claim that has not appeared on a remittance advice within 45 days of submission. That check matters because the regulation measures timeliness by the Department’s receipt of the claim.
A 2017 announcement from the Office of Developmental Programs, summarizing 55 Pa. Code Section 1101.68, notes that receipt is evidenced by appearance of the claim on a remittance advice. It also describes PROMISe edits labeled “Claim Past Filing Limit” and “Claim Past 365 Day Filing Limit.” Review each rejected claim for the reason before resubmitting, because a corrected claim must still land inside the 365-day period.
Put every submitted batch on a 45-day follow-up date when the remittance does not show the claims. A routine for tracking unpaid claims across payers makes that check automatic. Corrections also have their own limits, covered in our corrected claim deadline guide.
For a managed care denial, follow the plan’s dispute process, which has its own deadline. UPMC, for example, states appeal time frames on the explanation of payment. Our comparison of filing and appeal limits separates the two clocks, and denial management support keeps dispute dates visible when volume grows.
Why Can a Low Average Hide a Risky Service Line?
A blended days-to-submit average can look comfortable while one service line uses most of a shorter window, so every payer and claim group needs its own measure. The metric is the percentage of the filing window used, calculated per group.
Formula: Percent of window used = average days from service to submission ÷ filing window. Blended average = sum of (claims × average days) ÷ total claims.
Illustrative scenario (not an actual client record): a practice submits 1,000 Pennsylvania Medicaid claims in a month across three groups. Actual figures vary by practice.
| Claim group | Claims | Avg. days to submit | Window (days) | Percent of window used |
| Fee-for-service | 250 | 30 | 180 | 16.7% |
| Managed care, general claims | 600 | 22 | 180 | 12.2% |
| Managed care EPSDT claims (90-day plan rule) | 150 | 58 | 90 | 64.4% |
| Blended | 1,000 | 29.4 | n/a | n/a |
The blended figure is (250 × 30 + 600 × 22 + 150 × 58) ÷ 1,000 = 29.4 days. Against a 180-day window, that is 16.3% of the window, which looks very safe. The EPSDT group, however, uses 64.4% of a 90-day window, so one slow week pushes those claims past the plan’s limit.
How to use these numbers correctly
Compare like for like: judge fee-for-service claims against 180 days and EPSDT claims against the plan’s own 90-day rule. One group above 50% of its window is a signal to investigate the cause, such as slow charge entry or missing referral data, not a verdict on the team. Review monthly when volume is steady, and weekly when a new plan or service line starts.
How Quickly Can a Practice Tighten Pennsylvania Medicaid Billing?
Most practices see partial improvement within two to three months and fuller results within three to six months. These are general planning ranges, not guarantees, and they vary with claim volume, staffing, backlog size and how quickly each plan’s windows are built into daily work.
- Plan-specific deadlines and alerts built into the billing system: roughly 2 to 4 weeks.
- Clearing unbilled claims, oldest dates of service first: roughly 30 to 60 days.
- Fewer timeliness denials in monthly reports: partial results often appear in 2 to 3 months.
- Stable performance across fee-for-service and every HealthChoices plan: commonly 3 to 6 months.
Which Timing Mistakes Hurt Pennsylvania Medicaid Claims Most?
Most timing losses come from a handful of repeatable errors, all preventable with checks at registration, charge entry and submission. Each fix below is tied to the condition that triggers it, so staff know exactly when to act.
- Treating 365 days as the first-submission limit. Use 365 days only for resubmissions and adjustments when a claim was already submitted on time.
- Missing the first 60-day step. Start the CAO or third-party request within 60 days of service when coverage is uncertain.
- Using one window for all plans. Assign deadlines by plan and by claim type when any manual lists a shorter rule.
- Assuming a submitted claim was received. Confirm a remittance advice entry, or resubmit when none appears within 45 days.
- Ignoring the coordination of benefits clock. File secondary claims within the plan’s own period, such as 60 days after primary payment at some plans.
- Relying on a “sent” status. Save the acceptance report when a clearinghouse shows a claim as submitted.
Quick Summary
- The Medicaid Pennsylvania timely filing limit is 180 calendar days from the date of service for original fee-for-service claims.
- Rejected claims and adjustments must be received within 365 days of service.
- A 180-day exception requires an eligibility or third-party request within 60 days of service, and a second request within 60 days of the notice.
- HealthChoices plan windows come from manuals and vary by claim type, including 90 days for some EPSDT claims.
- A practical internal target is filing within about 10 days of service and alerting at 50% of the window.
- Track percent of window used by claim group, because blended averages hide risk.
Self-Check: Is Your Pennsylvania Medicaid Process Protected?
Answer yes or no to each question below, then use the scoring guide to see how exposed your current process is to late-filing write-offs. Be honest about any answer that depends on one person’s memory rather than a system setting, because that kind of dependency is where deadlines usually slip.
- Do you verify eligibility and plan assignment for the date of service before billing?
- Does your system hold separate windows for fee-for-service and each HealthChoices plan?
- Have you confirmed each plan’s current manual for corrections, secondary claims and EPSDT claims?
- Are most claims filed within about 10 days of service?
- Do you flag unbilled claims at 50% of the window?
- Do you ask about Medicaid status at the visit and start CAO requests within 60 days when needed?
- Do you confirm a remittance advice entry, or resubmit after 45 days?
- Do you keep EOBs and third-party documentation for at least four years?
- Do you track resubmissions against the 365-day limit?
- Do you review average days to submit by claim group, not only as a blended number?
Scoring guide: 9 to 10 yes answers means the process is well controlled; keep the monthly review going. 6 to 8 yes answers means there are gaps; fix each “no” within 30 days. 5 or fewer yes answers means high exposure; review the claim backlog now and consider outside support.
When Does Pennsylvania Medicaid Billing Call for Outside Help?
In-house billing reaches its limit when payer rules multiply faster than staff can track them. Five signals usually appear first:
- Timeliness denials recur despite reminders.
- Staff cannot list unbilled claims by plan and claim type on demand.
- Eligibility problems surface after the 60-day exception steps have passed.
- The payer mix includes fee-for-service Medicaid and several HealthChoices plans with different rules.
- Accounts receivable aged beyond 90 days keeps growing; our A/R management service addresses that backlog.
When comparing outside partners, look for payer-level reporting, a named contact, a maintained payer rules library, written escalation steps and a US-based team familiar with Pennsylvania Medicaid. Ask how deadlines are assigned, who monitors them and how exception documentation is stored.
EON MED SOLUTIONS is one example. The team provides end-to-end billing, coding, credentialing, denial management and compliance support through a US-based team with transparent reporting and no hidden fees. Results vary by practice. Review EON MED SOLUTIONS’ billing and RCM services to see how that process works.
Expert Opinion
The Medicaid Pennsylvania timely filing limit begins with 180 days, but the full picture includes 365 days for resubmissions, a two-step 60-day exception process and plan-specific rules under HealthChoices. Matching each claim to the right clock at registration solves most of the problem.
Firm, published standards in this guide are the 180-day, 365-day and 60-day periods in 55 Pa. Code Section 1101.68 and DHS guidance, plus the 45-day remittance check. Plan windows come from named manuals and vary by contract. The 10-day target, the 50% alert and the improvement timeframes are practical targets, and every worked example is illustrative.
The natural next question is which of your Pennsylvania Medicaid claims are closest to a deadline today, and which clock each one is running, since the answer decides what to work first. Talk with EON MED SOLUTIONS about a Medicaid timely filing review to find out.
Frequently Asked Questions
What is the timely filing limit for Pennsylvania Medicaid?
Pennsylvania Medicaid fee-for-service requires original claims to be received within 180 calendar days of the date of service under 55 Pa. Code Section 1101.68. Rejected claims and adjustments must be received within 365 days. HealthChoices managed care plans set their own windows in provider manuals and contracts.
How long do you have to resubmit a rejected Pennsylvania Medicaid claim?
A rejected original claim, or an adjustment, must be received by the Department within 365 days of the date of service. Nursing facilities and ICF/MR providers count 365 days from the last day of each billing period. Managed care plans may use shorter correction windows, so check the plan manual.
Can Pennsylvania Medicaid grant an exception to the 180-day limit?
Yes, in two cases: an eligibility determination was requested from the County Assistance Office within 60 days of service, or payment was requested from a third-party insurer within 60 days of service. The exception request must then reach DHS within 60 days of the determination or insurer response date.
What is a good internal filing target for Medicaid claims?
A common practical target is filing most Medicaid claims within about 10 days of service, with an alert at 50% of the applicable window. These are industry conventions, not Medicaid requirements. Track the percentage of window used by claim group so shorter plan rules, such as 90-day EPSDT limits, stay visible.
What is a good timely filing denial rate?
No standards body publishes a target for Medicaid timely filing denials. Because late filing is largely preventable, many practices treat any recurring denial as a process failure. Review denial counts monthly by plan and claim type, and investigate when average submission time passes half of that group’s filing window.
What should you do if a claim never appears on a remittance advice?
DHS advises resubmitting a claim that has not appeared on a remittance advice within 45 days of submission. Because the regulation measures timeliness by the Department’s receipt of the claim, confirm the original submission date, check the remittance, and resubmit well before the 180-day limit passes.
Sources and Methodology
(a) Published standards and definitions from named bodies
- Pennsylvania Code, 55 Pa. Code Section 1101.68, Invoicing for services.
- Pennsylvania Department of Human Services, FAQ: Medicaid Billing & Claims Status, including the 180-day exception process and Medical Assistance Bulletin 99-18-08.
- Pennsylvania DHS, Benefit Recovery notice on Medicare Part A and Part B billing, and DHS presentation on HealthChoices MCO credentialing (April 2024).
- Pennsylvania Office of Developmental Programs, Announcement 037-17, Process for 180-Day and 365-Day Timely Filing Edits (May 2017).
- AmeriHealth Caritas Pennsylvania Community HealthChoices, Billing Information page; UPMC Health Plan Provider Manual, Chapter H, Claims Procedures (updated October 28, 2024).
- 42 CFR 447.45 (state Medicaid claim filing) and 42 CFR 424.44 (Original Medicare filing limit).
(b) Named benchmarking data providers
- None used. No benchmark provider publishes a Pennsylvania Medicaid timely filing denial rate that this article relies on.
(c) Practical or illustrative targets from general industry practice
- The 10-day filing target, 50% alert point, improvement timeframes and every worked example are practical or illustrative figures, not Medicaid requirements.
(d) Survey or study data
- None used.
Methodology. Research was completed in October 2026. Third-party billing guides from ClaimMax RCM, MedStates, GenMediTech, MedPrecision and Medical Billing Service Near Me were compared against 55 Pa. Code Section 1101.68, DHS guidance and plan manuals. Where they conflicted, the primary document governed, and unresolved differences, such as plan-by-plan managed care windows, are stated in the text. Results vary by claim type, payer and contract. Figures reflect information available at the time of research; confirm current terms in the latest DHS handbook and each plan’s manual.


