

Medicaid Michigan Timely Filing Limit: The 12-Month Rule, Exceptions and Deadlines for 2026
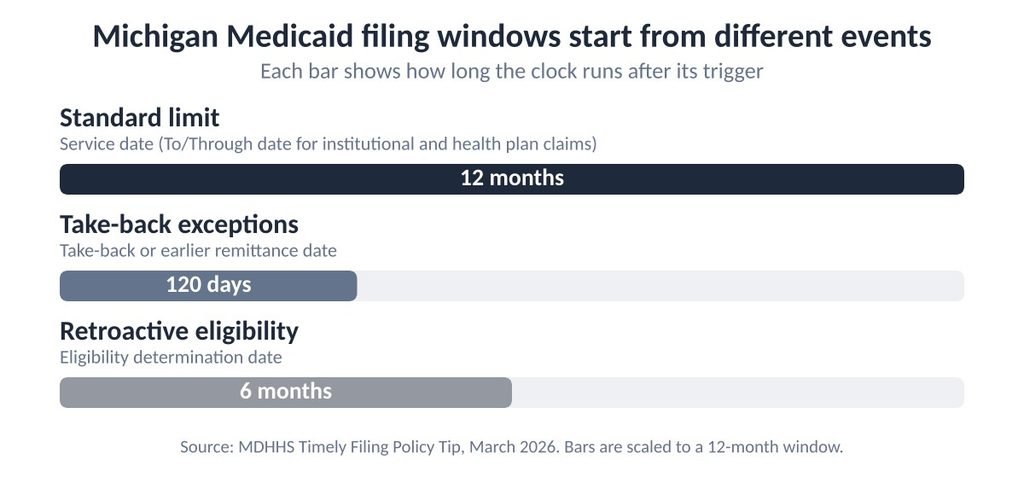
The Medicaid Michigan timely filing limit is 12 months from the date of service. The Michigan Department of Health and Human Services (MDHHS) measures that window by the claim’s transaction control number, and uses the “To” or “Through” date for institutional and Medicaid Health Plan claims. Older claims are considered only under seven documented exceptions.
Most Michigan billers already know the number is 12 months. The costly errors sit around it: the wrong start date for institutional claims, 120-day exception windows that begin at a take-back, and health plan manuals that differ from fee-for-service. This guide lays out the Medicaid Michigan timely filing limit, the seven exceptions MDHHS recognizes, and how Medicaid Health Plans differ. It also gives four calculations to run today, plus a self-assessment checklist near the end.
Michigan Medicaid filing numbers at a glance
| Metric | Practical target/range | Review frequency | Source type |
| Federal ceiling for provider claims | 12 months from the date of service | Annually | A |
| Michigan fee-for-service claim limit | 12 months from service; institutional and health plan claims use the To or Through date | At each MDHHS policy update | A |
| Replacement claims for late or added charges | Within 12 months of the date of service | At each policy update | A |
| Take-back and predictive-modeling exceptions | 120 days from the take-back or earlier remittance | Per event | A |
| Retroactive eligibility exception | Up to 6 months after the eligibility determination date | Per event | A |
| Meridian (Michigan) initial claims | 365 days from the date of service (2024 manual) | At each manual update | A |
| Priority Health claim billing limit | 12 months from the date of service (page updated 6/20/25) | At each manual update | A |
| Claim note length CHAMPS reads | First 80 characters | Per exception claim | A |
| Claim submission turnaround | Within 30 days of service for 95% or more of claims | Weekly | C |
| Aging alerts for unpaid claims | 90, 180 and 270 days from service | Daily worklist | C |
Source types: A = published government or payer source (MDHHS, federal regulation, plan manuals). B = named benchmarking data provider (none used in this article). C = practical planning target from common industry practice. D = survey or study data (none used). Plan rules change, so confirm against the current manual.
Medicaid Michigan timely filing limit explained: the 12-month rule
Michigan Medicaid requires claims to be resolved within 12 months of the date of service, a limit MDHHS describes in its Timely Filing Policy Tip, updated March 2026. The rule traces to bulletin MSA 16-37, issued November 30, 2016 and effective January 1, 2017, which set the limit at no later than one calendar year from the date of service. The MDHHS Timely Filing Policy Tip cites the Medicaid Provider Manual and CARC 29.
Federal regulation sets the ceiling. 42 CFR 447.45(d)(1) requires the state Medicaid agency to make providers submit all claims no later than 12 months from the date of service. Michigan’s rule matches that ceiling, so a claim past 12 months needs a documented exception, not an extension request.
Which date starts the 12 months?
The start date depends on the claim type. Each claim receives a transaction control number (TCN) showing when CHAMPS, Michigan’s Medicaid billing system, received it, and the TCN drives active claim review. For institutional claims and Medicaid Health Plans claims, MDHHS uses the “To” or “Through” date on the claim. For all other providers, the date the service was rendered or delivered starts the clock.
In billing audits, a common pattern is that teams count 12 months from the billing date or the first submission instead of the service or through date. Build each deadline from the claim’s own date field, and recalculate it whenever a claim moves between claim types.
Seven exceptions that reopen the clock
MDHHS recognizes seven exceptions that let a claim older than 12 months be considered, and each carries its own window and documentation. Claims need a comment or note, and CHAMPS reads only the first 80 characters of it. Retroactive provider enrollment is not an exception, according to bulletin MSA 16-37.
| # | Situation | Window | What to attach or note |
| I | MDHHS administrative error, or eligibility or authorization set retroactively more than 12 months after service | No window stated; the MDHHS caseworker submits form MSA-1038, and the provider bills after approval | Note that the MSA-1038 approval is on file |
| II | Third-party liability (TPL take-back) recovery; provider rebills | 120 days from the take-back pay-cycle date | Insurer letter or EOB; note the take-back TCN and date |
| III | Retroactive disenrollment from a Medicaid Health Plan | 120 days from the plan’s take-back; rebill to fee-for-service | Upload the take-back EOB in the CHAMPS Document Manager Portal |
| IV | Medicare, private or group insurer retroactively changes coverage and takes back payment | 120 days from the take-back | Upload the take-back document in the portal |
| V | MDHHS or contractor error, such as an incorrect prior authorization | No window stated; upload written proof before filing | Note that documentation of the error was submitted |
| VI | Delay caused by predictive modeling review of an earlier claim | 120 days from the earlier claim’s remittance date | Note the delay and cite the earlier claim’s TCN |
| VII | Retroactive eligibility or authorization | Up to 6 months after the retroactive determination date | Note that the claim is submitted for timely filing consideration |
Source: MDHHS Timely Filing Policy Tip, updated March 2026. Exceptions I and VII both involve retroactive changes, so read the tip to see which applies.
In billing audits, a common pattern is that exception claims are denied because the note is missing, truncated or buried after the 80th character. Put the exception reference first, then the TCN, and keep the supporting document in the portal before the claim goes out.
The windows run from the event date, not from the day staff notices it. A take-back letter that sits in a mailbox for three weeks consumes three weeks of a 120-day window, so date-stamp every take-back and eligibility notice on arrival.
Fee-for-service or health plan: whose deadline applies
MDHHS applies the 12-month limit to Medicaid Health Plan claims by their To or Through date, yet each plan’s manual states its own initial, corrected and appeal windows. The table shows examples, not a full plan list, so check the current manual for every plan you bill.
| Payer or program | Initial claim window | Corrections or appeals | Source |
| Michigan Medicaid fee-for-service | 12 months from service; To or Through date for institutional claims | Replacement claims within 12 months of service | MDHHS tip, March 2026 |
| Meridian Medicaid | 365 days from service | Resubmission: 365 days from service or 120 days from last remit, whichever is later | Meridian Claims Provider Manual, Oct. 2024 |
| Priority Health Medicaid and Healthy Michigan Plan | 12 months from service | Resubmit a claim not found in Claims Inquiry within 45 days of the original submission | Priority Health manual, updated 6/20/25 |
| Medicare fee-for-service (comparison) | 12 months from service | See our Medicare guide linked below | Medicare claims processing rules |
| Medicare Advantage and commercial | Set by contract | Set by contract | Your participation agreement |
Meridian’s manual also sets appeals at 365 days from service or 120 days from the explanation of payment, whichever is later. Figures reflect the editions named; confirm the current version.
Healthy Michigan Plan claims run through the same health plans, so treat them as Medicaid claims unless a plan manual says otherwise. A practice billing several plans should keep one row per plan, with the manual date, in a deadline table. Our guides to the Medicaid Texas 95-day rule and the Medi-Cal timely filing limit show how other state programs set shorter or different windows.
When Medicare or a private insurer pays first, the Policy Tip sets no separate crossover deadline. The closest guidance is Exception IV, so confirm crossover handling with MDHHS Provider Support and read our guide to secondary claim timely filing deadlines. For payer-by-payer habits, keep the payer-specific claim submission rules beside your deadline table.
Replacement claims: where the old and new descriptions differ
Bulletin MSA 16-37 described replacement claims as resubmittable within 12 months of the latest remittance advice date or other activity. The current Timely Filing Policy Tip states that replacement claims for late or additional charges must be filed within 12 months of the date of service. When the two differ, follow the current tip and treat the original service date as the controlling date.
Exceptions use different mechanics. When a TPL take-back occurs on a service more than a year old, the tip says to submit a new claim, not a replacement bill type. Our guide to corrected claim timely filing deadlines compares how other payers handle the same situation.
Four calculations to run before a claim ages out
Four short calculations turn the rules into dates and rates. Run the first three on any claim older than 90 days, and the fourth every month. Each uses the formula first, then an illustrative scenario with real numbers, so your team can copy the method into a spreadsheet.
Calculation 1: the 12-month deadline
Formula: deadline = service date (or through date for institutional and health plan claims) + 12 months.
Illustrative scenario (not an actual client record): a hospital stay runs from December 1 to December 10, 2025. The through date is December 10, 2025, so the deadline is December 10, 2026. On October 16, 2026, 55 days remain. A claim still unbilled with 55 days left belongs on a daily worklist.
Calculation 2: a take-back exception window
Formula: exception deadline = take-back pay-cycle date + 120 days.
Illustrative scenario (not an actual client record): a TPL take-back posts with a pay-cycle date of August 20, 2026. Adding 120 days gives December 18, 2026. On October 16, 2026, 63 days remain, which is enough time to gather the insurer letter and the take-back TCN.
Calculation 3: a retroactive eligibility deadline
Formula: exception deadline = retroactive determination date + 6 months, per Exception VII in the MDHHS tip (bulletin MSA 17-44 gives background).
Illustrative scenario (not an actual client record): a service on February 12, 2025 has retroactive eligibility determined on September 8, 2026. The standard 12 months ended February 12, 2026, before the determination. Exception VII allows filing up to 6 months after the determination, which gives March 8, 2027, if the claim note cites the retroactive eligibility.
Calculation 4: the on-time submission rate
Formula: on-time rate = claims submitted within 30 days of service ÷ total claims × 100.
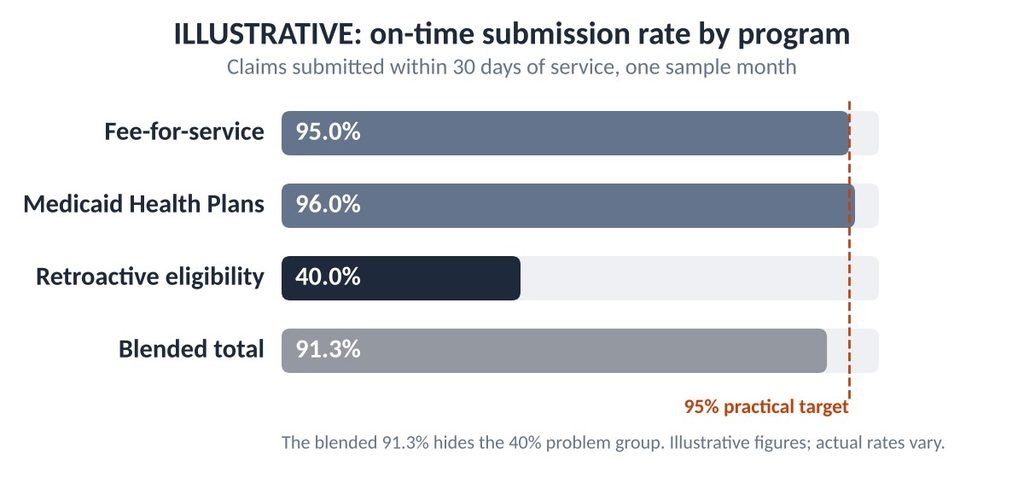
Illustrative scenario (not an actual client record): one month of Michigan Medicaid claims, split by program, shown beside the blended total that most dashboards report. The split matters because each program has a different trigger event.
| Program (Illustrative) | Claims | Submitted within 30 days | On-time rate |
| Fee-for-service | 220 | 209 | 95.0% |
| Medicaid Health Plans | 150 | 144 | 96.0% |
| Retroactive eligibility accounts | 30 | 12 | 40.0% |
| Blended total | 400 | 365 | 91.3% |
Illustrative figures; actual rates vary by practice, specialty and plan mix.
The blended 91.3% looks close to a 95% practical target. The retroactive eligibility line at 40% is the real problem, and a single combined number would hide it. Review each program separately whenever one group has a different trigger event from the rest.
Reading the results without fooling yourself
Compare like for like. Fee-for-service claims and plan claims run on different manuals, and retroactive eligibility accounts run on a different trigger, so each deserves its own row. One missed benchmark is a signal to investigate, not a verdict on the billing operation.
When a rate falls below target, check three things before changing the process: whether the deadline was calculated from the right date field, whether the delay sat in registration or in rejections, and whether the claims share a trigger event such as a take-back. A cluster of late claims from one month often traces to one cause, such as a staffing gap or an eligibility batch.
When a claim is already late: the recovery path
A claim past 12 months is denied with CARC 29, the claim adjustment reason code for an expired filing limit, unless it carries a recognized exception and a documented note. Bulletin MSA 16-37 states that claims submitted more than a year after service without remarks are denied.
Michigan providers must keep records that prove timely filing and supply them on request, because the payer decides whether a claim was on time. Proof of timely filing typically includes clearinghouse acceptance reports, CHAMPS remittances and payer acknowledgments. Follow these steps when a claim is already past 12 months:
Proof of timely filing
- Confirm the 12-month date from the service date or the through date, not the billing date.
- Match the claim to one of the seven exceptions, and confirm the exception window has not closed.
- Gather the required document, such as a take-back EOB or an MSA-1038 approval, and upload it before filing when the exception requires that.
- Submit with the claim note placed in the first 80 characters, then track the response.
In billing audits, a common pattern is that rebills after a retroactive health plan disenrollment stall because the 120-day window started at the take-back and no one dated it. A claim with no exception may still deserve appeal review, and our explainer on timely filing versus appeal filing limits separates the two clocks. A team facing a backlog may want help with denial management.
Separately, Michigan’s Medicaid timely payment law, Public Act 187 of 2000, requires qualified health plans to pay clean claims within 45 days, as summarized by Michigan State Medical Society legal counsel. A provider generally cannot resubmit the same claim before that period ends unless correcting a defective claim. The summary is undated, so confirm current law with your plan.

A tracking routine for Michigan Medicaid claims
A workable routine has six steps, and each step runs on a trigger condition, such as a new plan, a changed claim type or a dated notice arriving in the mailbox:
- Build a deadline table by program: fee-for-service, each Medicaid Health Plan and Healthy Michigan Plan, with the manual date beside each row.
- Calculate each claim’s deadline from its own date field, and recalculate when the claim type changes.
- Submit within 30 days of service as a practical target, and save the acceptance report; our tips on reducing claim rejection rate cover the common causes.
- Flag unpaid claims at 90, 180 and 270 days from service, using the method in tracking unpaid claims across payers.
- Start a dated exception clock on any take-back, EOB or retroactive eligibility notice the day it arrives.
- Review CARC 29 denials monthly by program, and refer aging balances past 270 days to A/R management support when the in-house team cannot clear them.
For a fuller setup, see how to track timely filing deadlines step by step in our guide. Pair that routine with Medicare’s rule, explained in the Medicare 12-month rule guide, when the same patient has both coverages.
How long until the routine shows results?
These are general planning ranges, not guarantees. Alerts and a program-level worklist often reduce last-minute submissions within two to four weeks. Because the standard window is 12 months, three to six months of data is a reasonable horizon for judging denial trends, and a full year confirms whether exception claims are being worked on time.
Mistakes that turn good claims into CARC 29 denials
- Counting from the billing date. Use the service date, or the through date for institutional and health plan claims.
- Assuming one number fits every plan. Read each Medicaid Health Plan’s current manual when you add or renew a plan.
- Missing the 120-day clocks. Date-stamp every take-back and start the exception window that day.
- Writing a weak claim note. Put the exception reference in the first 80 characters.
- Treating retroactive provider enrollment as an exception. MDHHS states it is not one.
- Relying on a generic state table. Verify any “365 days” figure against MDHHS wording before using it.
Quick summary
- The Medicaid Michigan timely filing limit is 12 months from the date of service.
- Institutional and Medicaid Health Plan claims use the To or Through date.
- Seven exceptions exist; most run 120 days from a take-back, and retroactive eligibility runs up to 6 months.
- Health plan manuals set their own windows, as the Meridian and Priority Health examples show.
- A practical target is submission within 30 days of service for 95% or more of claims.
- Track on-time rates by program, because a blended number hides weak spots.
Self-assessment: is your Michigan Medicaid process safe?
Answer yes or no to each question below, then count your yes answers and compare the total with the scoring guide that follows the list:
- Do you calculate deadlines from the service date, or the through date for institutional claims?
- Do you keep a deadline row for every Medicaid Health Plan you bill, with the manual date?
- Do 95% or more of claims go out within 30 days of service?
- Do you flag unpaid claims at 90, 180 and 270 days?
- Do you date-stamp take-back and eligibility notices on the day they arrive?
- Do you start a 120-day exception clock on every take-back?
- Do you put the exception reference in the first 80 characters of a claim note?
- Do you store proof of timely filing for every Medicaid claim?
- Do you track on-time rates separately for each program?
- Do you review CARC 29 denials monthly?
Scoring guide: 9 to 10 yes answers suggests a well-controlled process, so review it quarterly. 6 to 8 yes answers suggests gaps; fix the “no” items first, starting with questions 1 and 5. 0 to 5 yes answers suggests high exposure to timely filing denials and a good moment for an outside review.
When outside billing help makes sense
Outside support is worth considering when the in-house approach has reached its limits, and these five signals suggest that point has arrived for a Michigan Medicaid practice:
- CARC 29 denials appear in the same program more than one month in a row.
- Take-back and retroactive eligibility notices are not dated when they arrive.
- Staff cannot name the filing window for each Medicaid Health Plan the practice bills.
- Aging claims past 270 days build up faster than the team can clear them.
- Deadline tracking depends on one person’s spreadsheet.
Look for a billing partner that keeps a written deadline table by payer, reports on-time rates by program, retains proof of filing and works exception claims against a dated calendar. Transparent reporting and clear pricing matter as much as the deadlines.
EON MED SOLUTIONS is one example: a US-based team that delivers medical billing, coding, credentialing, denial management and A/R follow-up with transparent reporting and no hidden fees. Results vary by practice. You can review the EON MED SOLUTIONS billing, coding and RCM services to see how the work is organized.
Expert Opinion
The Medicaid Michigan timely filing limit is simple to state and easy to miscalculate. The firm published standards in this guide are the federal 12-month ceiling, MDHHS’s 12-month limit with its To or Through date rule, the seven documented exceptions and their windows, and each plan manual’s own published terms. Everything else is a practical target: the 30-day submission goal and the 90, 180 and 270 day alerts.
The worked examples are illustrative scenarios, not client results. They show how to turn a rule into a date, and how a blended rate can hide a 40% subgroup. Because MDHHS updates its policy tip and plans update their manuals, recheck the numbers each year and whenever a plan changes.
The natural next question is which of your Medicaid programs has no dated exception clock today. If the answer is several, a team that works claims and take-backs daily can help; start with EON MED SOLUTIONS’ billing and RCM services.
Frequently asked questions
What is the Medicaid Michigan timely filing limit?
Michigan Medicaid requires claims within 12 months of the date of service, measured from the To or Through date for institutional and Medicaid Health Plan claims. Claims past 12 months are considered only under documented exceptions, such as take-backs or retroactive eligibility. Confirm each health plan’s manual, because plan windows can be stated differently.
Is the Michigan Medicaid limit 365 days or 12 months?
MDHHS words the rule as 12 months, or one calendar year, from the date of service. Many billing sites quote 365 days without a source. The two are nearly identical, but build deadlines from the MDHHS wording and the claim’s own date field, and use the earlier date when a plan manual says 365 days.
What is a good claim submission turnaround for Michigan Medicaid?
A practical target is submitting most claims within a few business days, with 95% or more out within 30 days of service. This is an industry planning target, not an MDHHS requirement. Early filing leaves most of the 12-month window in reserve for rejections and corrections.
What is a good on-time submission rate for Medicaid claims?
No published benchmark exists. A practical goal is 95% or more of claims within 30 days of service, tracked separately for fee-for-service, each health plan and retroactive eligibility accounts. When one group falls well below the blended rate, investigate that group’s trigger event first.
What is a good aging alert schedule for Michigan Medicaid claims?
Many practices flag unpaid claims at 90, 180 and 270 days from the date of service. This is a planning schedule, not an MDHHS rule. The 270-day flag leaves about three months to resubmit or document an exception before the 12-month limit.
How do Medicaid Health Plan deadlines differ from fee-for-service?
Fee-for-service follows the MDHHS 12-month limit, while each Medicaid Health Plan publishes its own manual. Meridian’s 2024 manual lists 365 days from service, with resubmissions allowed up to 120 days after the last remit if later. Priority Health lists 12 months. Confirm the current manual for every plan.
Sources and methodology
(a) Published standards and definitions from named bodies
- MDHHS Provider Relations, Medicaid Timely Filing Policy Tip, updated March 2026: michigan.gov.
- MDHHS bulletin MSA 16-37, “Timely Filing Billing Limitation,” issued November 30, 2016, effective January 1, 2017.
- MDHHS bulletin MSA 17-44, issued December 1, 2017, effective January 1, 2018 (retroactive eligibility clarification).
- 42 CFR 447.45(d)(1), Timely claims payment: Cornell Legal Information Institute.
- Meridian Michigan Claims Provider Manual, October 2024: Meridian PDF.
- Priority Health provider manual, claim deadlines and timely filing, updated 6/20/25: Priority Health.
(b) Named benchmarking data providers. None used in this article.
(c) Practical or illustrative targets from general industry sources
- Industry state-by-state timely filing guides (MedStates, Arrow, OneMed Billing, GenMeditech, Manifest Technology Solutions) were reviewed for how competitors present Michigan. Several give 365 days or 12 months without a Michigan source, so this article relies on MDHHS wording instead.
- Michigan State Medical Society legal counsel, “Enforcement of Michigan’s Medicaid Timely Payment Law” (undated), for Public Act 187 of 2000 and the 45-day clean claim payment period.
- The 30-day submission goal, the 95% target and the 90, 180 and 270 day alerts are practical planning targets. All worked-example figures are illustrative.
(d) Survey or study data. None used in this article.
Methodology: the research reviewed the top results for the keyword, MDHHS policy documents and bulletins, federal regulation and two Michigan Medicaid Health Plan manuals in October 2026. The MDHHS tip cites the Medicaid Provider Manual section differently from the 2017 bulletin, so confirm the current section number in the manual. Results vary by program and plan, and figures reflect information available at the time of research. Confirm every deadline against the current MDHHS policy and your plan manuals.


