

Corrected Claim Timely Filing Limit: Deadlines by Payer
A corrected claim timely filing limit is the deadline to submit a replacement claim after the original was processed. Payers may count it from the date of service, the original remittance, or the finalization date. Original Medicare does not reset its 12-month clock for corrections.
A corrected claim can still be denied as late. Many teams assume a fix gets a fresh deadline, and some payers do allow extra time. Others count from the original service date and give none. This guide explains how the corrected claim timely filing limit works. It shows which clock start applies and how to protect it. You will find published payer examples, worked date calculations, and a workflow you can follow. A short self-check near the end tests your process. Every figure is labeled by source.
Corrected Claim Timely Filing Limit at a Glance
| Metric | Practical Target/Range | Review Frequency | Primary Source |
| Original Medicare: adding a missed item | Not permitted after the initial 12-month filing period | Per correction | ¹ Published federal standard |
| Original Medicare: reopening a timely claim | 1 year for any reason; up to 4 years with good cause | Per correction | ¹ Published federal standard |
| Highmark corrected claims | 455 days (15 months) from finalization of the original claim, effective Sept. 1, 2026 | At policy updates | ⁴ Published payer policy |
| Security Health Plan corrections | Normal filing limit or 60 days from payment, denial, or rejection, whichever is later | At policy updates | ⁴ Published payer policy |
| Other commercial and Medicare Advantage plans | Commonly reported 90 days to 15 months; start point varies | At contract signing | ² Commonly reported range |
| Internal correction target | Corrected claim filed within about 14 days of the remittance | Weekly | ³ Illustrative target |
¹ Published federal standard: CMS manuals and Medicare regulations. ² Commonly reported range: industry sources differ, so verify each contract. ³ Illustrative target: a practical planning figure, not a payer requirement. ⁴ Published payer policy: a named payer’s own published rule, which applies only to that payer.
What Counts as a Corrected Claim?
A corrected claim replaces or cancels a claim the payer already received. On the CMS-1500 form, frequency code 7 replaces a prior claim and code 8 voids it. The original reference number goes in the same field. The NUCC instructions tell billers to follow each payer’s own guidance, and some payers use other codes or portals. A wrong code can send the submission down the wrong path. That delay counts against your deadline, so confirm the payer’s method before you submit.
Rejected Claims and Denied Claims Differ
The distinction changes the clock. A rejected claim never entered adjudication, so the payer may treat the first submission as never filed. You fix the error and resubmit inside the original filing limit. A claim that was denied or paid was processed. A change then becomes a corrected claim, a reopening, or an appeal. Each path has its own deadline. Sort every returned claim into one of these groups before you calendar anything. Record the group beside the claim so the next person sees it.
Medicare Corrections Follow Finality Rules
Original Medicare does not give corrections a new filing window. The CMS Claims Processing Manual bars adding a forgotten item or service after the initial filing period closes. A correction that only fixes information on a timely claim falls under reopening rules instead. Medicare allows a reopening request within one year of the initial determination for any reason. Good cause extends that to four years. Contractors decide these requests at their discretion, so file early and document the reason. Keep the remittance date with the claim record.
Worked example 1: adding a missed service line
Formula: Last day to add an item = date of service + 1 calendar year (next workday if it lands on a weekend).
A service occurs on January 8, 2027, and the claim is filed in February. The team then notices a missed service line. The one-year mark is Saturday, January 8, 2028, which moves to Monday, January 10, 2028. After that date, Medicare will not accept the added item. A wrong modifier is different. That is a reopening question, with its own timeline.
Commercial and Medicare Advantage: Three Clock Starts
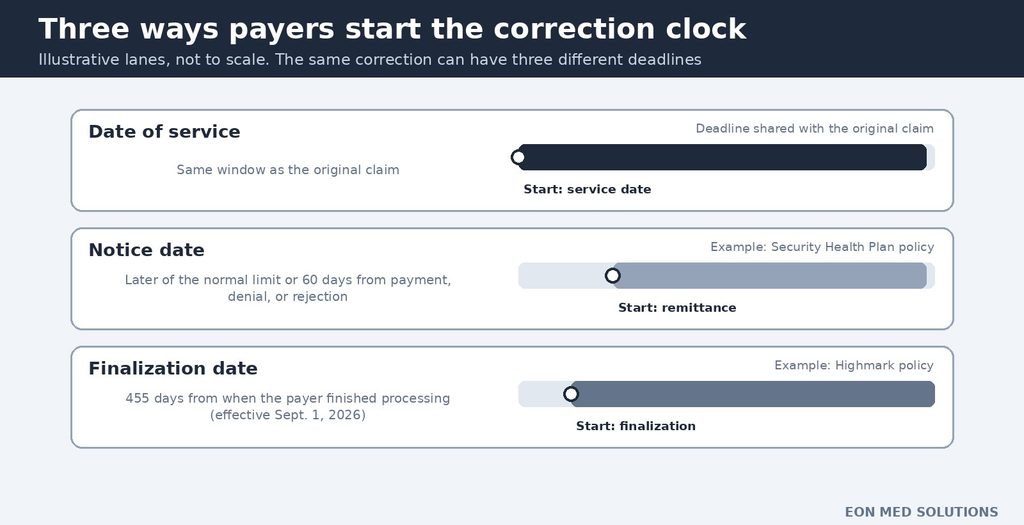
Outside Original Medicare, the rule lives in each payer’s manual or contract. Most fall into three patterns, shown below. Published policies illustrate them, but each applies only to the named payer. Industry sources also disagree on some large payers. One reports a 180-day corrected-claim window from remittance for a national carrier. It also notes that the payer’s own guidance points to a service-date basis. Treat your contract as the controlling document, and verify before you rely on any secondary figure.
| Clock start | How the deadline works | Published example |
| Date of service | The correction must arrive inside the same window as the original claim | Common in contracts; confirm wording |
| Payment, denial, or rejection date | The window runs from the notice date; some plans allow the later of two dates | Security Health Plan policy |
| Finalization date of the original claim | The window runs from when the payer finished processing the original | Highmark policy, effective Sept. 1, 2026 |
Worked example 2: a finalization-based deadline
Formula: Deadline = finalization date + 455 days.
Illustrative scenario (not an actual client record): a payer finalizes an original claim on October 15, 2026. The payer uses a 455-day rule. Adding 455 days gives Thursday, January 13, 2028. A team counting from the service date would track the wrong deadline. Record the clock start beside each payer. Confirm which claims the rule covers before relying on it.
A Correction Workflow That Protects the Deadline
A short, repeatable routine keeps corrections from turning into late claims. Assign it to one owner, and review it every week. Good front-end habits help too, because fewer errors mean fewer corrections. These claim submission tips and a clean claim rate plan reduce the volume that needs fixing. Even so, some corrections are unavoidable, so the routine needs to be fast. Keep the steps below on one page where the whole billing team can see them. Speed matters because every day counts.
- Classify the returned claim as rejected, denied, or paid with an error.
- Find the payer’s rule and the date that starts its correction clock.
- Calculate the deadline, then set an internal target well before it.
- Submit with the right frequency code and the original reference number.
- Confirm the payer accepted the correction, and file the proof.
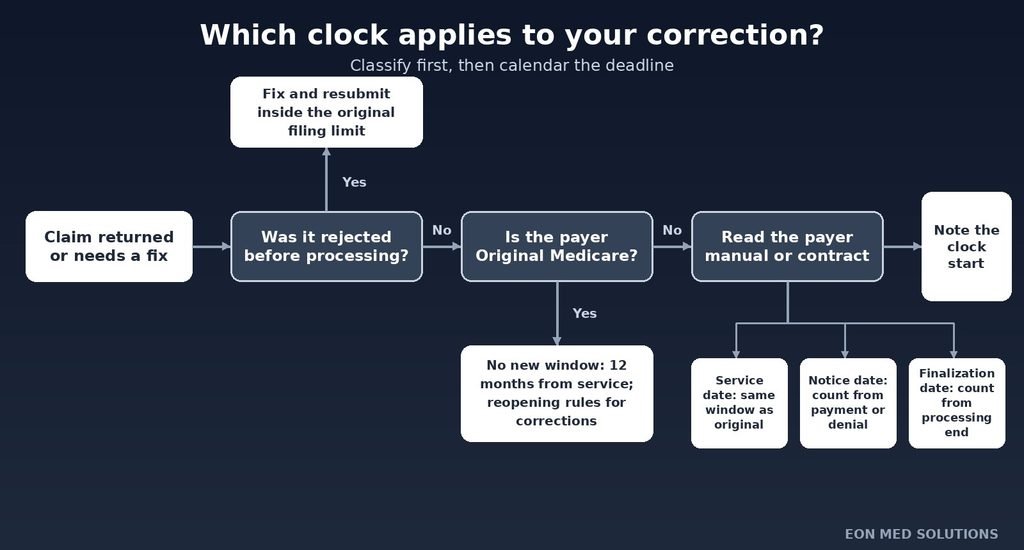
Late corrections often arrive as denials, so pair this routine with structured denial management. It helps decide whether a fix, a reopening, or an appeal is the right path. Log every correction with its original submission date and remittance date. Two dates now matter instead of one. Store both beside the payer’s clock-start rule, so anyone can calculate the deadline. Review the log weekly, not only when a denial appears. This habit also shows patterns, such as one payer returning many claims.
Worked example 3: blended on-time correction rate
Formula: On-time correction rate = corrections filed within the window ÷ total corrections × 100.
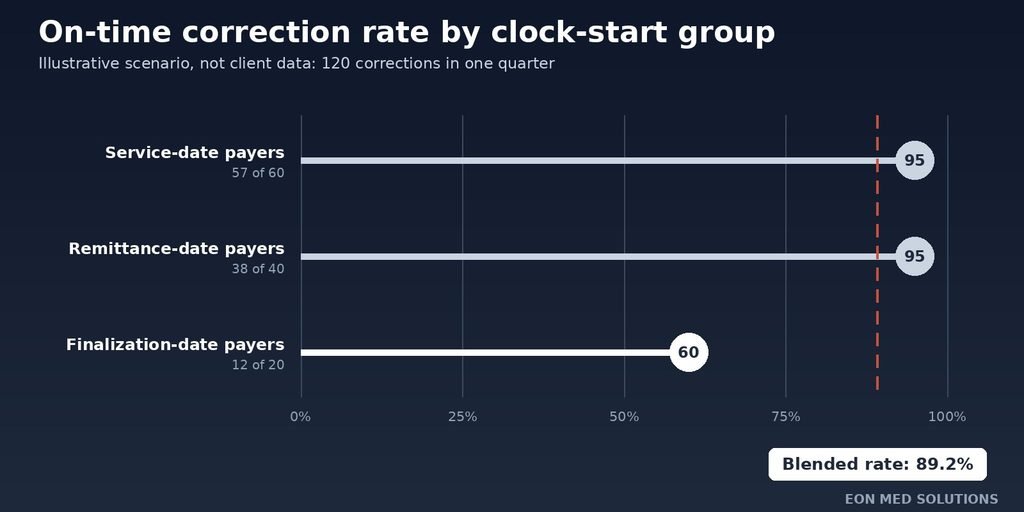
Illustrative scenario (not an actual client record): a practice files 120 corrections in a quarter. Service-date payers show 57 of 60 on time, and remittance-date payers show 38 of 40. Finalization-date payers show 12 of 20. The blended rate is 107 ÷ 120, or 89.2%, which looks close to 90%. Yet only 60% of finalization-based corrections were on time, and the average hides it.
Reading These Numbers Like for Like
A deadline is meaningful only against the right clock start. Compare Medicare with Medicare, and one payer’s policy with that payer’s own past results. Do not compare a 455-day finalization rule with a 90-day service-date rule directly. The 14-day internal target is a planning figure, not a payer rule. One missed correction is a signal to check your dates, not a verdict on the team. Start with the payer group that misses most often. Keep each comparison inside one payer group.
How Fast Correction Tracking Improves?
Illustrative planning ranges only. They are not guarantees, and results vary by practice.
| Fix | Partial Results | Fuller Results | What It Takes | Key Constraint |
| Clock-start field per payer | 1–2 weeks | 1–2 months | Reading manuals and contracts | Locating current policies |
| Correction log with two dates | 2–3 weeks | 1–3 months | Recording original and remittance dates | Consistent data entry |
| Weekly correction review | 2–4 weeks | 2–3 months | A fixed slot and one owner | Staff time |
The Short Version
- Original Medicare does not reset its 12-month clock for corrections (published federal standard).
- Medicare reopenings run one year for any reason and up to four with good cause.
- Other payers count from service, remittance, or finalization, so record each one.
- Highmark and Security Health Plan rules apply only to those payers.
- A 14-day internal correction target is a practical goal, not a payer mandate.
Self-Check: Are Your Corrections Protected?
Answer yes or no to each question, then read the scoring guide below.
- Do you record each payer’s correction clock start in writing?
- Do you separate rejected claims from claims that need correction?
- Do you log both the original submission date and the remittance date?
- Can you list open corrections by days remaining in under an hour?
- Do you know Medicare’s reopening windows?
- Do you submit corrections with the required frequency code and reference number?
- Do you confirm the payer accepted each correction?
- Does one person own the correction queue?
- 7–8 yes: Well protected. Review payer policies quarterly.
- 4–6 yes: Gaps exist. Fix the “no” answers first, starting with questions 1 to 3.
- 0–3 yes: At risk. Audit open corrections by deadline this week.
Expert Opinion
The firm parts of the corrected claim timely filing limit are narrow. Medicare does not reopen the filing window for corrections, and its reopening periods come from federal rules. Highmark and Security Health Plan figures are firm only for those payers, and only as published. Everything else is practical or illustrative, including the 14-day target, the improvement timeframes, and the commonly reported ranges. Payers update these rules, as Highmark’s 2026 change shows. Verify each contract yourself, and review your payer matrix every quarter.
One pattern is worth naming directly. Teams treat a correction as the end of a problem, so the clock stops getting attention. In practice, a correction starts a second deadline. Payers count it from different points, and the second date often lives in a different report. Logging both dates in one place closes that gap. Assign that log to one person, and review it weekly. It also supports better A/R management, because corrected claims stay visible until they are paid.
Frequently Asked Questions
corrected claim timely filing limit
What is the corrected claim timely filing limit?
It is the deadline for submitting a replacement or void claim after the original was processed. It depends on the payer, and some count from service, remittance, or finalization.
Does a corrected claim reset timely filing?
Not for Original Medicare, where corrections do not restart the 12-month window. Other payers vary, so check the clock start in your contract.
What is the Medicare timely filing limit for corrected claims?
There is no separate window. The 12-month filing limit applies, and corrections to timely claims follow reopening rules of one year, or four with good cause.
What is the difference between a rejected claim and a corrected claim?
A rejected claim never entered adjudication and is fixed and resubmitted. A corrected claim replaces one the payer already processed, often with frequency code 7.
Which frequency code shows a corrected claim?
The NUCC form uses 7 to replace and 8 to void, with the original reference number. Payers may add their own rules, so follow their instructions.
What is a good internal deadline for corrected claims?
No standard exists. Many teams aim to file within about 14 days of the remittance, an illustrative target that leaves a buffer.
What is a good on-time correction rate?
No official benchmark exists. Many practices aim for close to 100%, as an illustrative goal. Track it by payer, because a blended rate can hide weak groups.
What happens if a corrected claim is filed late?
The payer usually denies it for timely filing. Options are limited and depend on the payer’s policy, so document the dates and check for exceptions.
When Correction Tracking Outgrows Your Team?
Watch for these signals that your correction process has reached its limits:
- Corrections are filed near a deadline, or after it, without anyone noticing.
- Nobody can say which date starts each payer’s correction clock.
- Corrected claims disappear from reports once they are resubmitted.
Look for support that treats a correction as a new deadline, not a closed case. Ask how a partner logs the original and remittance dates, who owns the correction queue, and how corrected claims appear in A/R reports. Confirm HIPAA safeguards and clear reporting. EON MED SOLUTIONS is one option to evaluate on those points. Its US-based team pairs end-to-end medical billing, coding, credentialing, denial management, and A/R management, so a correction can be followed through rather than handed off. It emphasizes transparent reporting and no hidden fees. Results vary by practice and situation, so compare its services against your self-check results.
Sources and Methodology
- Published standards: CMS Claims Processing Manual, Chapter 1, Section 70 (Rev. 12909); 42 CFR 405.980 (reopenings); NUCC 1500 Claim Form Reference Instruction Manual (Item 22).
- Named payer policies: Highmark provider news (updated July 24, 2026) and the Security Health Plan provider manual. Each applies only to that payer.
- Practical or illustrative targets: the 14-day target, improvement timeframes, and both illustrative scenarios. Other commercial windows are commonly reported industry ranges that disagree.
- Named benchmarking data providers and surveys: none used.
Actual results vary by practice and situation. Figures reflect information available in September 2026, so verify current rules with each payer before acting.


One Comment